

Airway & Sleep
How well you breathe is determined, in large part, by how your face is built.
The width of the dental arch, the position of the tongue, the development of the jaw and midface—these structural realities shape the space available for the airway. When that space is compromised, the consequences are felt throughout the body: disrupted sleep, chronic fatigue, morning headaches, difficulty concentrating, and a jaw and face that compensate in ways that show over time.
Airway and sleep concerns span a spectrum—from primary snoring and upper airway resistance syndrome (UARS) to obstructive sleep apnea. Craniofacial structure can play an important role across this spectrum, and understanding how the airway is shaped and supported is central to how we evaluate and treat these conditions.
Do you recognize any of these?
The signs of a compromised airway are not always obvious. Many patients have lived with these patterns for so long they have accepted them as normal:
Loud or chronic snoring
Waking unrefreshed despite adequate sleep
Morning headaches
Excessive daytime sleepiness or fatigue
Difficulty concentrating or memory problems
Waking with a dry mouth or sore throat
Observed pauses in breathing during sleep
Chronic jaw tension, clenching, or grinding
Mouth breathing

Why this matters
Sleep disordered breathing—across the full spectrum from snoring to sleep apnea—is not simply a sleep problem. When breathing is repeatedly disrupted during sleep, the body activates a stress response—elevating cortisol, straining the cardiovascular system, and disrupting the hormonal and metabolic processes that depend on restorative rest.
Untreated sleep disordered breathing has well-documented associations with:
High blood pressure
Heart attack and stroke
Diabetes
Depression and anxiety
Memory loss and dementia
Sexual dysfunction
Weight gain
Accelerated aging
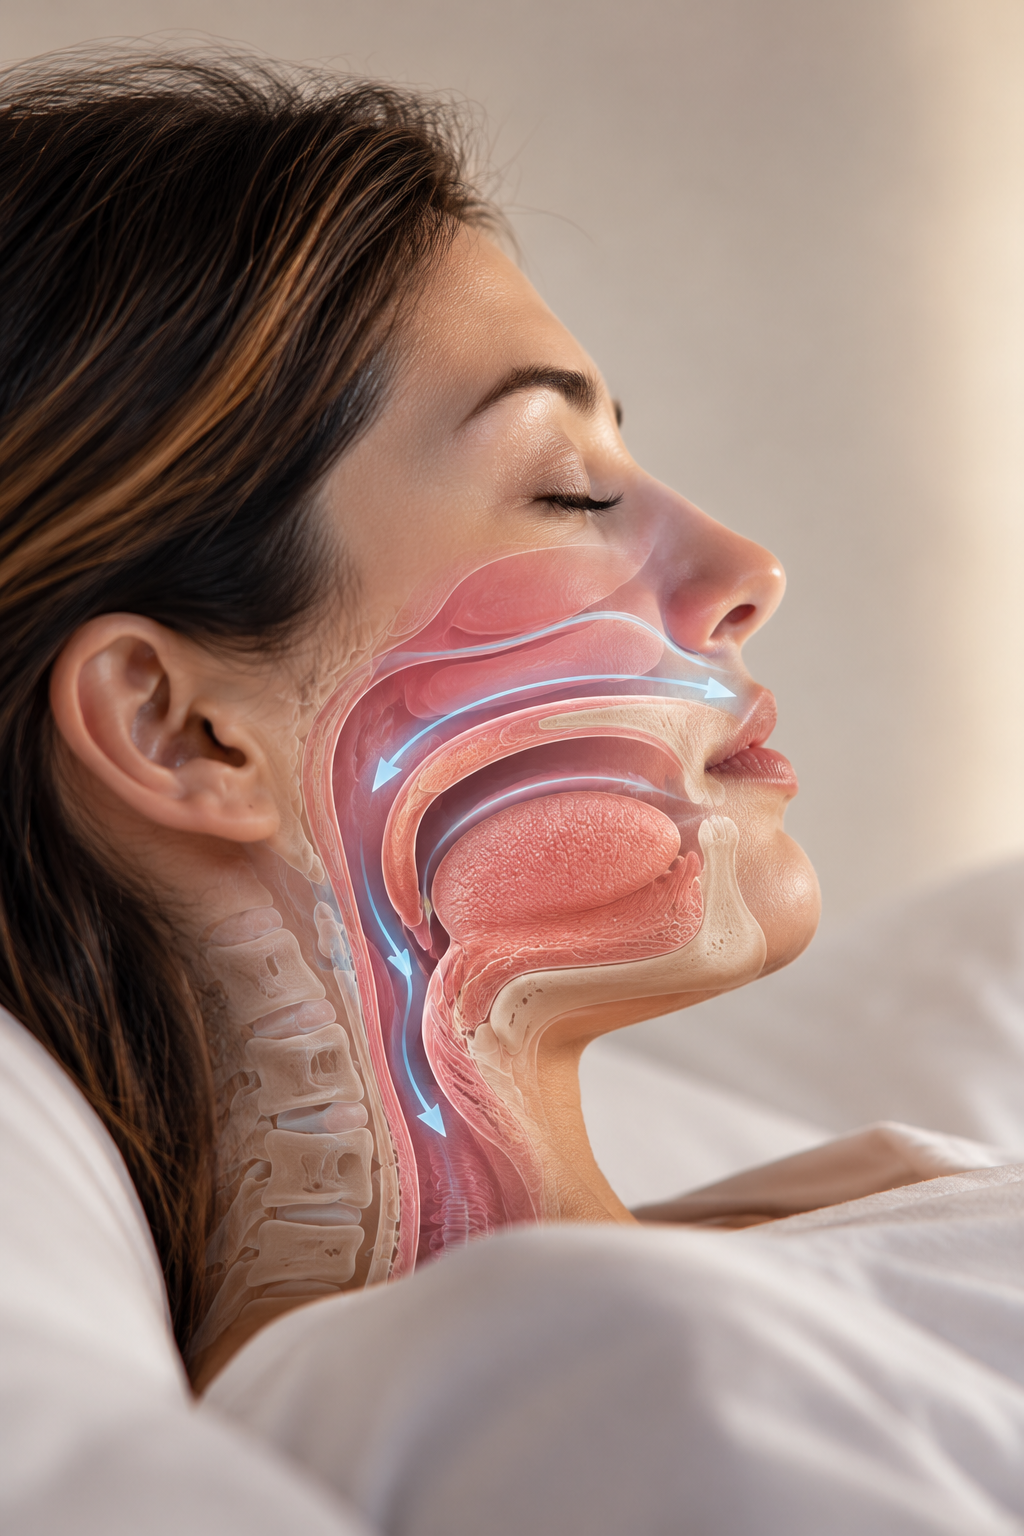
Structure shapes the airway.
The airway is not an isolated system. It is defined by the bones, tissues, and muscles that surround it—the arch width, the palate, the position of the tongue at rest, the development of the jaw.
A narrow arch limits tongue space. A restricted tongue posture can influence how the airway develops and functions during sleep. Mouth breathing, snoring, and disrupted sleep can be manifestations of structural patterns rooted in craniofacial anatomy.
Understanding this connection changes how airway problems are assessed and treated. Interventions that manage symptoms without considering underlying anatomy may leave important contributing factors unaddressed. Structural interventions—expanding the arch, releasing a restricted tongue when indicated, or correcting the bite—can address those factors directly.
Sleep disordered breathing.
Sleep disordered breathing is a spectrum. At one end, primary snoring—disruptive, often dismissed, but a sign that the airway is working harder than it should. In the middle, upper airway resistance syndrome (UARS)—a condition in which repeated airway narrowing fragments sleep and produces significant daytime symptoms, frequently without meeting the threshold for an apnea diagnosis. At the far end, obstructive sleep apnea—repeated complete or partial airway collapse during sleep, with measurable drops in oxygen.
Patients across this entire spectrum can experience the same consequences: unrefreshed sleep, chronic fatigue, cognitive impairment, mood changes, and the systemic health effects of disrupted breathing night after night. Many have been told their snoring is not a medical problem. It is.
Diagnosis begins with a sleep study, which can be coordinated in-house or patients may bring an existing study from their physician. The appropriate treatment is determined based on the findings and the structural factors involved.
QuietNite Laser Snore Treatment
Using fractional CO₂ laser energy, we stimulate collagen remodeling in the soft palate and surrounding tissues. The goal is to improve tissue firmness and reduce palatal flutter—the vibration of the soft palate that contributes to snoring.
This quick, painless, minimally invasive in-office treatment requires no incisions, no anesthesia, and little to no downtime. A simple, convenient option for patients looking to reduce snoring.
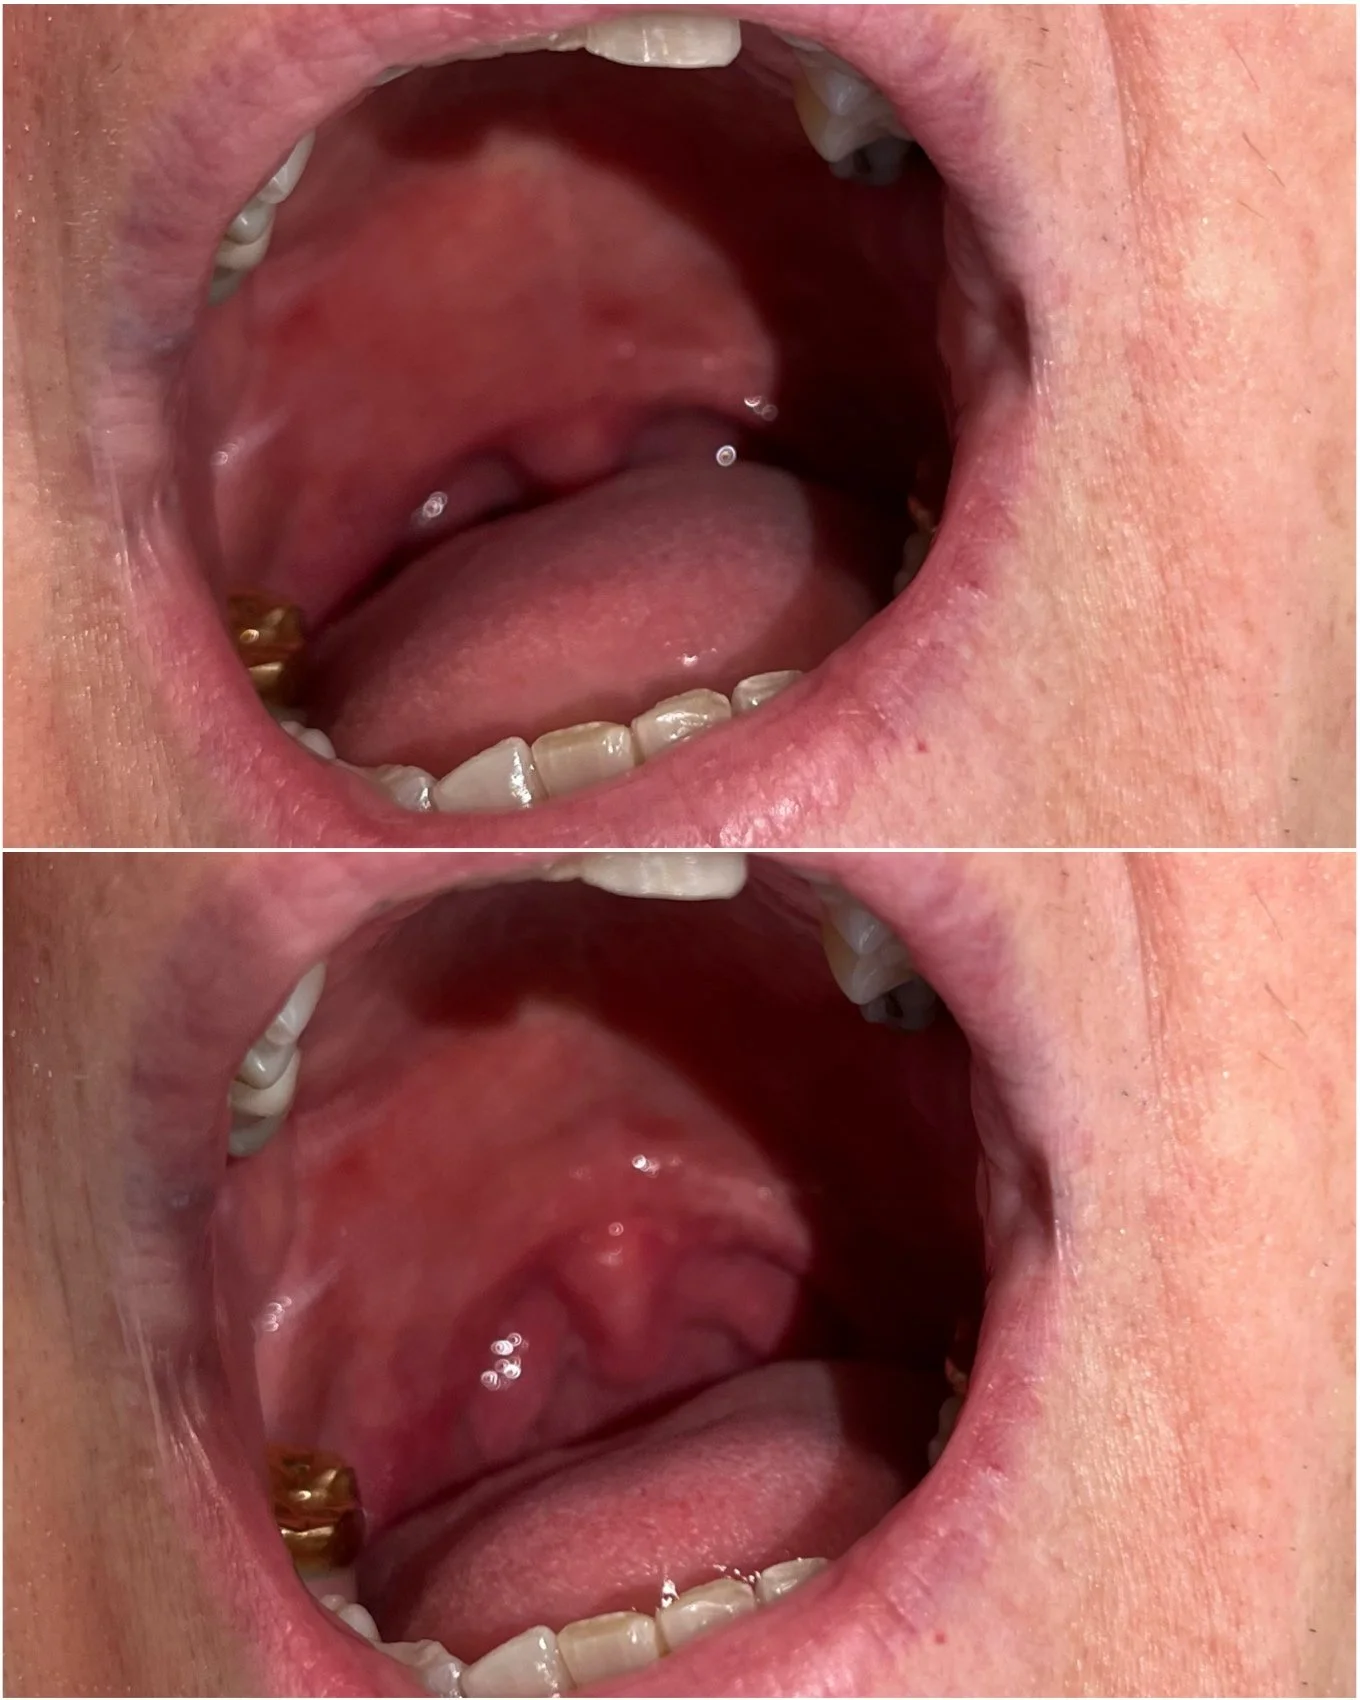
Oral appliance therapy.
Oral appliance therapy is an established, evidence-based treatment for snoring, upper airway resistance syndrome, and obstructive sleep apnea. A custom device worn during sleep repositions the lower jaw and tongue to help maintain an open airway.
For appropriate patients, oral appliance therapy offers an effective, comfortable alternative to CPAP, often with better patient adherence.
Patients with an existing sleep study can come in directly. For those without a prior diagnosis, sleep testing can be coordinated as part of the evaluation.
For patients whose airway restriction is rooted in structural narrowing of the arch or restricted tongue posture, structural intervention alongside appliance therapy addresses the cause, not just the symptom.

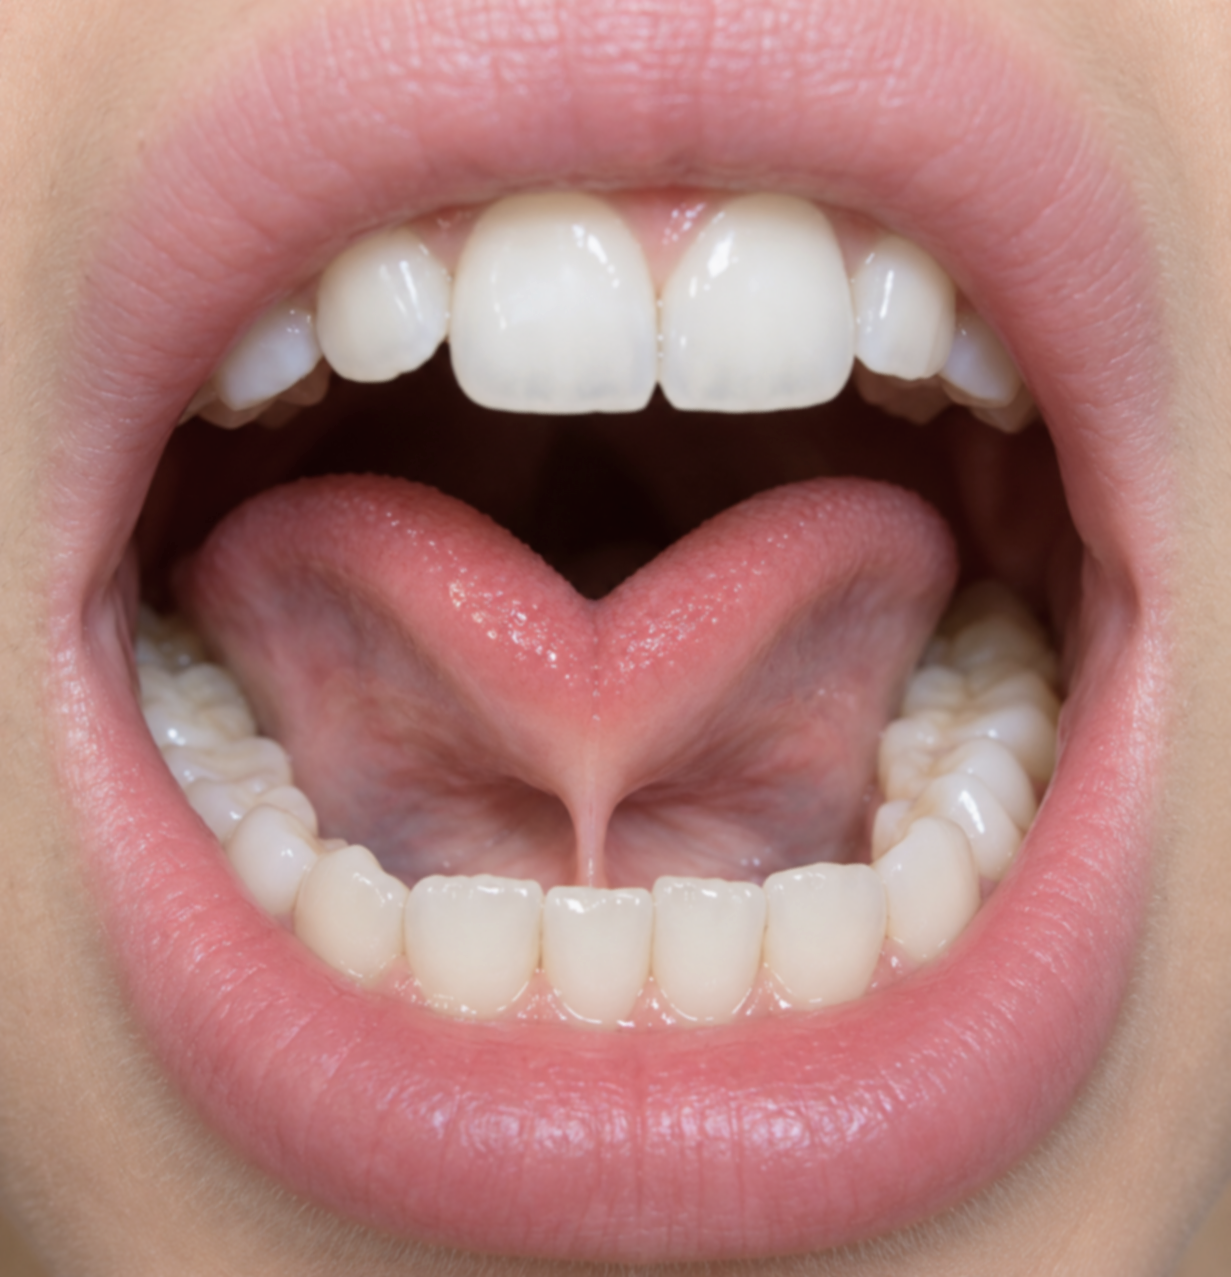
Tongue tie & Frenectomy.
A tongue tie—or ankyloglossia—is a restriction of the lingual frenulum that limits the range and mobility of the tongue. When the tongue cannot rest fully against the palate, it defaults to a lower posture that affects arch development, swallowing, breathing, and airway function during sleep.
The connection between tongue tie and airway is frequently overlooked. Patients with unresolved tongue ties often present with narrow arches, mouth breathing, snoring, forward head posture, and chronic jaw tension—patterns that persist unless the restriction itself is addressed.
Frenectomy—the release of the lingual frenulum—is performed here as a minimally invasive procedure. Release alone is most effective when combined with myofunctional therapy to retrain tongue posture and function following the procedure. Lip tie release is also available where indicated.
Treating the airway—
from symptom to source.
Oral appliance therapy helps maintain an open airway during sleep, but it does not change the underlying anatomy that may be contributing to airway restriction. For many patients, that distinction matters.
Treatment here addresses the airway at every level.
ORAL APPLIANCE THERAPYA custom device worn during sleep that repositions the jaw and tongue to maintain an open airway. Effective for snoring, UARS, and mild to moderate sleep apnea.
TONGUE TIE RELEASEReleasing a restricted lingual frenulum allows the tongue to assume its correct resting posture against the palate—reducing airway obstruction and supporting nasal breathing.
CLEAR ALIGNER THERAPY WITH ARCH EXPANSIONBroadening and rounding the arch through aligner treatment creates more tongue space and reduces airway restriction—with meaningful improvements in breathing and sleep for patients with mild to moderate narrowing.
LEARN MORE ABOUT CLEAR ALIGNER THERAPY →
GAPLESS ADULT PALATAL EXPANSIONFor patients with a significantly narrow arch, gapless palatal expansion addresses the structural origin of airway restriction directly. The arch is widened at the skeletal level—creating more tongue space, improving midface support, and changing the airway from the inside out. The aesthetic transformation to the smile and facial proportions is significant. The functional change to breathing and sleep can be life-changing. This is the most meaningful non-surgical airway intervention available to adults.
LEARN MORE ABOUT GAPLESS ADULT PALATAL EXPANSION →
Frequently Asked Questions
-
Yes. Snoring is a sign that the airway is working harder than it should—that airflow is being disrupted even if breathing is not fully stopping. Chronic snoring is associated with fragmented sleep, cardiovascular strain, and progressive airway narrowing over time. It also affects the sleep quality of anyone sharing a bed with you. Snoring alone warrants evaluation, independent of whether sleep apnea is present.
-
Upper airway resistance syndrome—UARS—is a condition in which the airway repeatedly narrows during sleep, causing the brain to briefly arouse from deep sleep to restore airflow. The arousals are too brief to be remembered but cumulatively prevent restorative rest. Patients with UARS often present with significant daytime fatigue, difficulty concentrating, mood changes, and unrefreshed sleep—without meeting the formal threshold for an apnea diagnosis. Many have been told their sleep study is normal. UARS is real, it is underdiagnosed, and it responds to the same structural and appliance-based treatments as sleep apnea.
-
Common signs include loud or chronic snoring, waking unrefreshed despite adequate sleep, morning headaches, daytime fatigue, difficulty concentrating, mood changes, and breathing pauses observed by a partner. Many patients also present with chronic jaw tension, clenching, forward head posture, and mouth breathing—all of which reflect the body compensating for a compromised airway. A sleep evaluation establishes where on the spectrum a patient falls and guides treatment accordingly.
-
CPAP delivers pressurized air through a mask to keep the airway open during sleep. It is effective but many patients find it difficult to tolerate consistently. An oral appliance repositions the jaw and tongue to maintain airway opening without a machine or mask. For snoring, UARS, and mild to moderate sleep apnea, oral appliances are an evidence-based option with equivalent outcomes in appropriate candidates and significantly better long-term compliance.
-
A narrow arch reduces the space available for the tongue, which adopts a lower posture—particularly during sleep—where it can partially obstruct the airway. This is one of the most common structural origins of snoring, UARS, and sleep apnea. Expanding the arch creates more tongue space and can meaningfully reduce airway restriction. For patients with significant narrowing, structural expansion alongside or instead of appliance therapy addresses the cause directly.
-
A tongue tie is a restriction of the lingual frenulum that limits tongue mobility and range. When the tongue cannot rest against the palate, it adopts a lower posture that affects arch development, nasal breathing, swallowing, and airway function during sleep. Adults with unresolved tongue ties frequently present with narrow arches, mouth breathing, forward head posture, and sleep disordered breathing—often without ever having been assessed for the restriction.
-
For patients whose airway compromise is related to restricted tongue posture, releasing the lingual frenulum—followed by myofunctional therapy to retrain tongue position—can meaningfully improve breathing, reduce snoring, and support better sleep. Results are most significant when frenectomy is part of a broader treatment plan that addresses arch width and tongue posture together.
-
Yes. Patients with an existing sleep study can come in directly to discuss oral appliance therapy. A review of the study, an assessment of the jaw and airway, and impressions for a custom appliance can all be completed at the initial appointment.
-
The face reflects its structural foundation. Patients with airway compromise often present with chronic jaw tension, masseter hypertrophy, forward head posture, and facial changes that accumulate over years of compensatory muscle activity and disrupted sleep. Addressing the airway changes how the face looks and functions—and the aesthetic work done alongside it is more effective, more stable, and more genuinely restorative as a result.
Comprehensive consultations across Rhode Island and Massachusetts.